
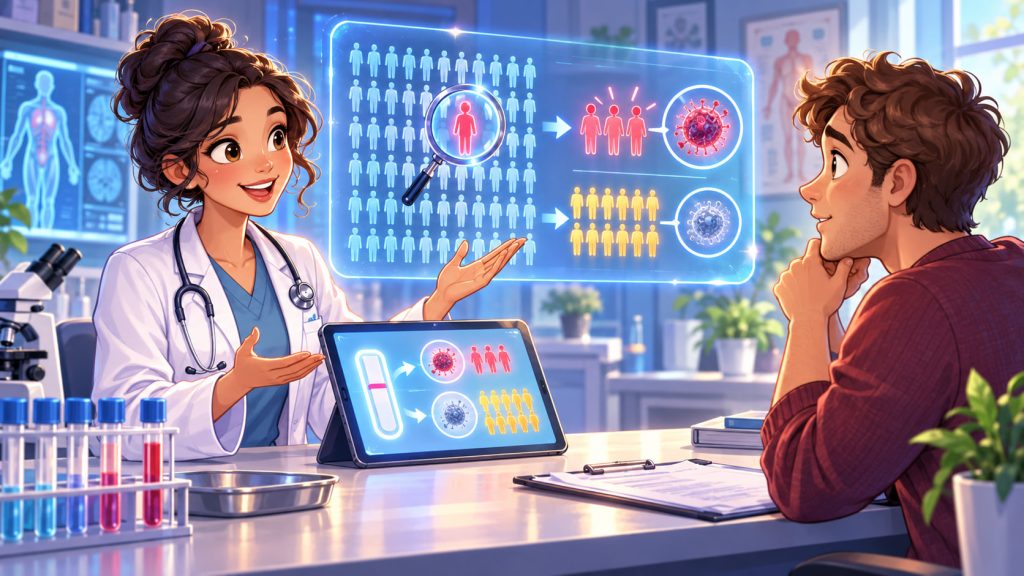
A positive medical test can be frightening. Many people naturally assume that if a test comes back positive, the disease is almost certainly present.
But that is not always true.
The meaning of a positive result depends not only on how accurate the test is, but also on how common the disease was before testing.
This is where Bayes’ theorem becomes extremely important.
Bayesian reasoning helps doctors interpret test results in context. It explains why even a highly accurate test can produce a surprising number of false positives when screening for a very rare condition.
A positive test changes the probability of disease. It does not automatically make that probability 100%.
What Is Bayes’ Theorem?
Bayes’ theorem is a mathematical rule for updating probability when new information becomes available.
In medicine, it helps answer a practical question:
How likely is a patient to actually have a disease after receiving a particular test result?
The answer depends on two broad things.
First, how likely the disease was before the test.
Second, how well the test distinguishes people with the disease from people without it.
This means the same positive result can have very different meanings in different patients.
The Importance of Pre-Test Probability
Before a test is performed, doctors already have some estimate of how likely a disease is.
This is called the pre-test probability.
It may be influenced by:
- Age
- Symptoms
- Family history
- Exposure history
- Other medical conditions
- Physical examination
- How common the disease is in the population
If a disease is extremely rare and a healthy person has no symptoms or risk factors, the pre-test probability may be very low.
If another person has classic symptoms and known risk factors, the probability may already be much higher.
Bayes’ theorem combines this starting probability with the test result.
Sensitivity and Specificity
Two important measures describe medical test performance.
Sensitivity is the proportion of people with the disease who receive a positive result.
A highly sensitive test misses relatively few true cases.
Specificity is the proportion of people without the disease who receive a negative result.
A highly specific test produces relatively few false positives.
These measures are important, but they do not directly answer the question most patients care about:
“If my test is positive, what is the chance I actually have the disease?”
That question requires information about disease prevalence or pre-test probability.
A Simple Example
Imagine a rare disease affecting 1 in 1,000 people.
Now imagine a screening test with:
- 99% sensitivity
- 99% specificity
Those numbers sound excellent.
Suppose 100,000 people are tested.
About 100 people would actually have the disease.
With 99% sensitivity, approximately 99 of them would test positive.
Now consider the 99,900 people who do not have the disease.
With 99% specificity, about 1% would falsely test positive.
That means roughly 999 healthy people could receive a positive result.
So among all positive results, there would be approximately:
- 99 true positives
- 999 false positives
A positive result would therefore not mean a 99% chance of disease.
The actual probability would be only around 9% in this simplified example.
That is the power of the base rate.
Why This Feels So Counterintuitive
People often focus on the test’s accuracy and ignore how rare the disease is.
If a test is described as “99% accurate,” it is tempting to assume that a positive result means a 99% chance of illness.
But that interpretation is usually incorrect.
The test is being applied to a population containing many more healthy people than sick people.
Even a small false-positive rate can produce a large number of false alarms when millions of healthy people are tested.
Rare diseases create a mathematical environment where false positives can outnumber true positives.
What Is a False Positive?
A false positive occurs when a test indicates that a disease or condition is present when it actually is not.
False positives can happen for many reasons.
Biological measurements naturally vary.
Laboratory instruments are not perfect.
Other conditions may produce similar markers.
Cutoff values can classify borderline results as positive.
No medical test is perfect in every patient.
A false positive does not necessarily mean the test is poor. It may simply reflect the unavoidable trade-offs involved in detecting disease.
Why Screening Programs Are Especially Affected
Bayesian reasoning is particularly important in population screening.
Screening means testing people who may have no symptoms.
Because many screened individuals are healthy, the starting probability of disease can be low.
This is why screening programs are carefully designed.
Doctors and public-health specialists consider whether early detection improves outcomes, how accurate the test is, what confirmatory tests are available, and whether unnecessary investigations could cause harm.
A screening test is often the beginning of diagnosis, not the final step.
Positive Predictive Value
The probability that a person truly has the condition after receiving a positive test is often described as the positive predictive value, or PPV.
PPV depends strongly on prevalence.
When a disease becomes more common in the tested population, a positive result is more likely to represent a true case.
When a disease is rare, the PPV can fall dramatically.
This is why a test may perform differently in a specialist clinic than in the general population.
Patients referred to a specialist may already have symptoms or risk factors, increasing their pre-test probability.
Why Doctors Order Confirmatory Tests
When an initial test is positive, especially for a rare or serious disease, doctors may perform another test.
The second test may use:
- A different laboratory method
- Imaging
- Genetic analysis
- Biopsy
- Repeat measurement
- A more specific diagnostic technique
This step can sharply improve diagnostic confidence.
If two independent tests both strongly support the same diagnosis, the probability can rise substantially.
Confirmatory testing helps prevent a single imperfect result from being treated as definitive evidence.
Bayes’ Theorem and Cancer Screening
Cancer screening provides a useful example.
A screening result may indicate increased suspicion, but it often does not prove cancer is present.
Additional imaging or tissue sampling may be required.
This is because screening programs usually aim to detect as many potentially important cases as possible.
That can mean accepting some false positives.
The balance is difficult.
Too many false positives create anxiety and unnecessary procedures.
Too many false negatives allow real disease to go undetected.
Bayes’ Theorem and Infectious Disease Testing
The same principle applies to infectious diseases.
If an infection is widespread in a community, a positive test may have a high probability of being correct.
If the infection is extremely uncommon, an unexpected positive result may deserve confirmation.
Timing also matters.
Testing too early or too late can influence detection.
Symptoms, exposure history, vaccination status, and local disease prevalence can all change the interpretation.
The result is therefore never completely separate from clinical context.
Expert Perspective
Clinicians and medical statisticians emphasize that tests should be interpreted as probability-changing tools rather than simple yes-or-no machines.
A result has meaning only when combined with the patient’s history, symptoms, risk factors, and the known performance of the test.
This is why experienced doctors do not usually diagnose complex diseases from one isolated number.
Bayesian reasoning is built into good clinical practice even when no one explicitly writes down Bayes’ theorem.
False Negatives Matter Too
Bayesian reasoning is not only about positive results.
A negative test can also be misleading.
If a person has a very high pre-test probability of disease, one negative result may not reduce the probability enough to rule the condition out.
For example, if symptoms are highly characteristic, a doctor may repeat the test or use a different diagnostic method.
The starting probability matters whether the result is positive or negative.
Why Testing Everyone Can Sometimes Cause Problems
It may seem logical to test as many people as possible for as many diseases as possible.
But widespread testing can create unintended consequences.
Very rare abnormalities will occasionally appear simply by chance.
False positives can lead to:
- Anxiety
- Repeat testing
- Additional imaging
- Biopsies
- Medical costs
- Incidental findings
- Unnecessary treatment
This does not mean screening is bad.
It means screening is most useful when the expected benefits outweigh the risks of false alarms and unnecessary intervention.
The Role of Natural Frequencies
Bayesian problems are often easier to understand using actual numbers rather than percentages.
Instead of saying:
“The disease prevalence is 0.1%, sensitivity is 99%, and specificity is 99%,”
imagine 100,000 real people.
Then count how many are sick, how many healthy people falsely test positive, and how many positive results exist in total.
This approach is called using natural frequencies.
It often makes probability much easier to understand.
Bayes’ Theorem Beyond Diagnosis
Bayesian reasoning appears throughout medicine.
Doctors continually update probabilities when new evidence appears.
A symptom changes the probability of a disease.
A blood test changes it again.
An imaging scan changes it again.
A biopsy may change it further.
Medicine therefore involves repeated updating.
Diagnosis is often a sequence of probability revisions rather than one dramatic moment of certainty.
Why a Positive Test Should Be Interpreted Calmly
A positive result can be important and should not be ignored.
But it should also not automatically be interpreted as a final diagnosis.
The next step depends on the test, condition, symptoms, and clinical situation.
For rare diseases in particular, confirmation may be essential.
Understanding Bayes’ theorem can reduce unnecessary panic while also showing why follow-up matters.
The correct question is not simply:
“Was the test positive?”
It is:
“Given everything we know before and after this test, how likely is the disease now?”
Interesting Facts
- A test with 99% sensitivity and 99% specificity can still produce mostly false positives when screening for an extremely rare disease.
- Disease prevalence strongly influences the positive predictive value of a medical test.
- The same laboratory result can mean different things in different patients.
- Screening tests are often designed to identify possible disease rather than establish a final diagnosis.
- Doctors routinely use Bayesian reasoning even when they do not explicitly calculate Bayes’ theorem.
- A negative test does not always rule out disease when the pre-test probability is high.
- Confirmatory testing can dramatically improve diagnostic certainty.
- Natural frequencies often make medical probability easier to understand than percentages.
- Population-wide testing can produce large numbers of false positives even with very good tests.
- Clinical history can sometimes be as important as the test result itself.
Glossary
- Bayes’ Theorem — A mathematical rule used to update the probability of an event when new evidence becomes available.
- Pre-Test Probability — The estimated likelihood that a patient has a condition before a test is performed.
- Post-Test Probability — The estimated likelihood of a condition after taking the test result into account.
- Sensitivity — The proportion of people with a disease who correctly receive a positive test result.
- Specificity — The proportion of people without a disease who correctly receive a negative result.
- False Positive — A positive test result in someone who does not actually have the condition.
- False Negative — A negative test result in someone who actually has the condition.
- Positive Predictive Value — The probability that a person with a positive test truly has the disease.
- Prevalence — The proportion of a population that has a particular condition at a given time.
- Screening — Testing people, often without symptoms, to identify possible disease at an early stage.
- Confirmatory Test — A follow-up test used to verify an initial result.
- Natural Frequencies — A way of expressing probabilities using counts of people or events rather than percentages.

